Archive Page 99

Vertigo is a Symptom, Not a Diagnosis, and it’s Sometimes Caused by Loose Rocks Inside Your Head

I often hear patients speak of vertigo as if it were some brilliant diagnosis made by a genius emergency room doctor. Just because it’s a foreign word, that doesn’t make it any more clever than if they’d been told they were dizzy.

In my native Sweden there seems to be a domestic lay word for almost every disease. The runner up prize in my book goes to FÖNSTERTITTARSJUKAN, “The Window Shoppers Disease”, which we call intermittent claudication, usually caused by poor blood flow to the legs (people feeel better if they stand still for a while, for example pretending to look in a store window) but occasionally we get tricked and the symptom can be caused by pressure on the spinal cord from disc disease.

I absolutely love the number one word on my Swedish Disease Names list: The word they use for the most common cause of true vertigo, “Benign Positional Vertigo” or BPV. The Swedish word is KRISTALLSJUKAN (The Crystal Disease).

I also love explaining to patients how it works, because I think the body is a pretty clever contraption.

Vertigo is the illusion of movement, a spinning or rotatory form of dizziness. It usually originates in the balance organ, called the labyrinth, in the inner ear. Two common causes of vertigo are labyrinthitis, which is a viral infection, and Benign Positional Vertigo, which I wish we also would call the Crystal Disease.

This is how it works:

The labyrinth has two parts, the otololith organ and the semicircular canals. They are connected and filled with a sort of hydraulic fluid that we call the endolymph. Each inner ear, left and right, has this setup, and normally they provide the brain with the same, consistent information on where in space we are – but not always.

The otolith organ has one chamber, the utricle, that registers movement along a flat surface, like me rolling around the exam room on my stool (that’s how I demonstrate this). I hold my hands up with fingers pointing to the ceiling. “There are nerve cells in the otolith organ with little hairs sticking up like this”, I explain. Touching each fingertip with my other hand, I continue “and there is a weight, a little crystal, attached to the top of each of these hairs. If I move like this (stool roll..) the crystals make the little hairs bend, actually exaggerating the movement so I can register the slightest change in my position along this level path…”

The other chamber in the otolith organ, called the saccule, is set up to register movement in a vertical plane. Here I scrunch down or straighten up as I sit on my stool.

The Semicircular canals are curved tubes running in three different planes. They have a wider portion at one end with hairy nerve cells, similar to the otolith organ but without the crystals. When we turn our heads, the endolymph (fluid) movement causes the little hairs in each of the three semicircular canals to move a little differently and bend the nerve cell hairs to a different degree and maybe even in a different direction. All this information gives the brain a detailed sense of where in space we are.

Sometimes the little crystals fall off the hairs they’re sitting on top of in the otolith organ and travel with the endolymph into the semicircular canals.

Imagine what happens if the balance organ on one side tells the brain “movement to the left, thirty degrees” (here, I make the fingers on my left hand wiggle in unison just a little) and the other side, because some crystals flattened the nerve cell hairs, reports “wow, we’re upside down” (right hand and arm making a slam dunk movement). For at least a brief moment, our poor brains believe the louder, more dramatic yet inaccurate alarm report and we feel quite ill from that.

This explains why, in Benign Positional Vertigo, head movements in one direction can be much worse than movements in a different direction, depending on which angle causes the most dramatic effect from the little crystals.

This situation can go away spontaneously as the crystals can end up randomly traveling away from where the nerve cells register them.

There are also head maneuvers that can force the crystals away from the semicircular canals. Physical therapists and doctors in the specialties that deal the most with dizziness can put people through these movements, and you can even find instructions online.

Here is one of the most comprehensive explanations of all this that I have come across:

Lastly, a clinical pearl from Harvard’s neurology professor Dr. Martin Samuels. In his classic lecture on dizziness, he warns us never to suggest specific aspects of this symptom when taking a history. Most patients with dizziness will say yes to any description you suggest to them, therefore making diagnosis nearly impossible. Instead, he calls on his physician audience to repeat the word “dizzy”, maybe even a few times, scratch their chin and fix their gaze on something outside the window while rubbing their chin now and them – for however long it takes – until the patient starts to describe their symptoms themselves. Once they do, the diagnosis usually presents itself very plainly.

Cultivating Charisma in the Clinical Encounter (and emulating Marcus Welby, M.D.)

If medical journals are the religious texts that guide me as a physician, the New York Times has become the secular source of illumination for my relationship to my country and the world I live in.

That doesn’t exactly mean that I feel like a citizen of the world. Quite the opposite, particularly now, with just me and my horses sharing our existence on a peaceful plot of land within walking distance of the Canadian border; my physical world seems quite small even though I am aware, sometimes painfully but with an obvious distance, of the calamity of our planet.

Early Sunday morning, drinking coffee in bed as the gray morning light revealed the outline of the trees and pasture outside my window, I read the Times on my iPad as usual and came across an article titled “What makes people charismatic and how you can be too”.

The article claims that charisma can be learned and cultivated, and that thought resonated with me as I think often about how we as physicians have roles to fill in the stories of diseases and transitions in our patients lives. I try to be the kind of doctor each patient needs as I walk into each exam room.

The article mentions three pillars of charisma: Presence, Power and Warmth.

As I think of my current third guiding light in addition to my medical journals and the New York Times, my DVD collection of the Marcus Welby, M.D. shows, which is shorthand for his character and all the other role models I carry mental images and video clips of, Charisma is definitely something we need to consider and cultivate in our careers.

My job, my reason for being, is to guide and motivate people, and how I come across, how people perceive me, helps determine my chances of filling that role.

So, these pillars of Charisma in the archetypal physician, in my case Marcus Welby, look somewhat like this – first quoting the Times:

“The first pillar, presence, involves residing in the moment. When you find your attention slipping while speaking to someone, refocus by centering yourself. Pay attention to the sounds in the environment, your breath and the subtle sensations in your body — the tingles that start in your toes and radiate throughout your frame.”

Marcus Welby was certainly a keen observer and a good listener. He was also aware of and in tune with his own feelings. Thinking back over my own writing, I recall posts like “The Power of Focus” and “Today’s Masterpiece”. This is about being present so you can connect with each patient, and also so you can do your best under whatever circumstances exist in that moment.

“Power, the second pillar, involves breaking down self-imposed barriers rather than achieving higher status. It’s about lifting the stigma that comes with the success you’ve already earned. Impostor syndrome, as it’s known, is the prevalent fear that you’re not worthy of the position you’re in. The higher up the ladder you climb, the more prevalent the feeling becomes.

The key to this pillar is to remove self-doubt, assuring yourself that you belong and that your skills and passions are valuable and interesting to others. It’s easier said than done.”

I think many of us are afraid to use the power we have and just as the Times article points out, power is not about status; in medicine it is about power to help, fix or influence. Consider their words “assuring yourself that you belong and that your skills and passions are valuable” – Marcus Welby certainly didn’t seem to doubt that when he spoke up to his hospital medical staff or to patients and families. He projected a quiet power and confidence that we, today, as cogs in the big healthcare machine may not always feel that we have. My own writing includes “Where is Relationship, Authority and Trust in Healthcare Today?” and “Getting it Right”.

“The third pillar, warmth, is a little harder to fake. This one requires you to radiate a certain kind of vibe that signals kindness and acceptance. It’s the sort of feeling you might get from a close relative or a dear friend. It’s tricky, considering those who excel here are people who invoke this feeling in others, even when they’ve just met.

To master this pillar, Ms. Cabane suggests imagining a person you feel great warmth and affection for, and then focusing on what you enjoy most about your shared interactions. You can do this before interactions, or in shorter spurts while listening to someone else speak. This, she says, can change body chemistry in seconds, making even the most introverted among us exude the type of warmth linked to high-charisma people.”

Marcus Welby, strict as he could be, exuded a well measured warmth, kindness and relatedness. I have speculated, for example in “Role Play”, that this warmth isn’t necessarily of our own making but emanating from the source of everything, whatever people may choose to call that.

When you get right down to it, I think healthcare providers today are too often viewed by others and increasingly also by themselves as interchangeable. That is the opposite of Charisma. Like so many times before in recent years, I’m puzzled by how everywhere else in our society people and businesses strive to stand out and to establish their constant presence, perceptions of power and warm relationships with their customers, while healthcare professionals are hiding too much behind a vail of sameness and anonymity, seemingly even creating distance and projecting a lack of warmth – almost on purpose in a misguided effort to seem professional?

A Country Doctor Reads: August 17, 2019

I Learned a New Word Today: RECRUDESCENCE – NEJM

The New England Journal of Medicine’s question of the week was about an elderly man with a prior stroke history, who during a febrile illness had a temporary recurrence of his original stroke symptoms.

“Patients who have had neurologic deficits as a result of stroke or multiple sclerosis sometimes experience reemergence or recrudescence of those deficits in the setting of an intercurrent illness. The most common triggers include infection, hypotension, hyponatremia, hypoglycemia, insomnia, stress, and benzodiazepine use. Recrudescence occurs most commonly with middle cerebral-artery infarcts and can lead to language, sensory, and motor deficits. Gaze preference, hemianopsia, and neglect are not typically observed.”

— Read on knowledgeplus.nejm.org/question-of-week/1860/

Diabetes Related Hospitalizations Not Necessarily Caused by Poor Outpatient Management – JAMA

Quality is an elusive thing: JAMA Network Open has a piece about what kind of correlation there is between the diabetes quality indicators we all deal with in primary care and what really happens to patients. Any guesses?

In this study, the associations among different types of diabetes quality measures were weak, and much variation in the rates of utilization-based outcomes was unexplained by clinical practice group performance on traditional process and disease control measures. This outcome may be due in part to the topped-out nature of process measures, but the weak association between clinically robust disease control measures and hospitalization rates, the modest difference in hospitalization rates based on process and disease control performance, and the small amount of variation between clinical practice group hospitalization rates explained by process and disease control performance all raise concern about the validity of utilization-based outcomes as a measure of quality in chronic diseases. In chronic diseases such as diabetes, more hospitalizations may not necessarily be evidence of poor outpatient care, which has significant implications for quality-based reimbursement in chronic disease management.

— Read on jamanetwork.com/journals/jamanetworkopen/fullarticle/2747756

Family health history: underused for actionable risk assessment – The Lancet

I’m making a plug again for The Lancet, which has lots of free material, available just by registering.

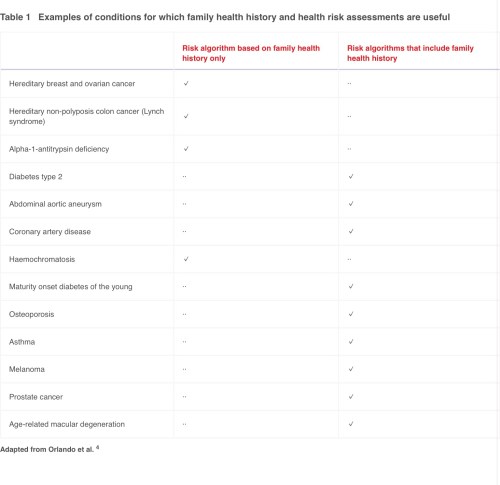
Here’s something so basic we should be ashamed for not making better use of: The FAMILY HISTORY. Now that there are genetic markers and all, why don’t we pay more attention to obtaining a proper Family History?

If applied across the general population, systematic FHH-based risk assessment has the potential to have a substantial effect on population health management. Up to 44% of people meet criteria for increased risk for at least one hereditary condition based on current guidelines, so the potential for impact on health is huge.40 Scaled to a population, FHH becomes a means of assessing the true risk and potential costs that a health system might use to better manage its financial risk. When multiplied to potentially affected family members, the effect becomes even greater.
— Read on www.thelancet.com/journals/lancet/article/PIIS0140-6736(19)31275-9/fulltext

Whom Does the EMR Serve? Who Owns and Who Needs THE STORY?

I have advocated before for putting a visit synopsis at the beginning of each visit note. I have called that the aSOAP note. I think that works immensely better than APSO notes that only rearrange the order of the elements. The reason I say that is that in today’s EMR notes, it’s too darn hard to find THE STORY. If a note is half a dozen pages or scrolls long, why would I want the medication changes and the reason why they were made at opposite ends of the note? The order means less than the distance between them in my opinion.

The way I approach reading a note is with the two questions “What happened in the last visit?” and “Why was that the clinical decision?” In more and more of my office notes I answer these two questions for future readers, which would include me, in temporal, typographical and spatial connection with each other, right on top.

Let’s face it, how often would it be more useful to try to scan a lengthy Review of Systems and a Comprehensive Exam to find the pertinent positives than to read in the top paragraph that the patient who was placed on a potassium sparing diuretic two months ago and kept rescheduling their followup appointment is now hypotensive and nauseous with an unusually pale complexion and putting out less than normal amounts of urine. Consequently we stopped the medication, sent the patient for STAT labs or to the ER. Seriously, I don’t need to read anything more in that office note: You and I both know this person is in acute kidney failure, caused by the spironolactone. DONT WASTE MY TIME AS A FUTURE READER by mixing those crucial elements with other, less pertinent information. Put it in there, away from the story in case somebody needs to check if we screened for depression or smoking status, but those are filler materials and side plots in this riveting STORY of iatrogenicity.

I admit that in today’s healthcare environment, the office note serves many “stakeholders” (I’m not sure I like that word…), but since I am the clinician who sees the patient, makes treatment plans and then has to follow up on what parts of the treatment plan worked and what parts didn’t, I can’t accomplish anything without the thread of the chain of events I am ending up calling THE STORY. It belongs to the patient, but I’m the one that needs it, desperately sometimes, as even small nuances in the narrative of a life or a disease can change my assessment and the trajectory of care I provide.

And, here’s a confession, if I don’t have time to finish my note in real time, or if (ahem) I’m catching up on a backlog of chart notes, it’s the “a for abstract” segment I focus on; the number of “bullets” and 99213 versus 99214 is not my priority when I’m in survival mode (mine AND possibly the patient’s).

So I am again making the case for a narrative abstract at the top of each office note, an executive summary if you will, just like the world of academic journals has decided to present complex information.

If it’s good enough for The New England Journal of Medicine, it should be good enough for this Country Doctor.

Passed a Stress Test With Flying Colors and Had a Heart Attack on the Way Home, How Could That Happen?

Tomorrow I’ll have another “Medical Monday” talk taped for our local TV station.

It’s set up more like an interview but I still have to prepare it like a talk. It’s a little speech I give to patients several times per week, but it still causes some raised eyebrows, so I think it’ll be useful for a bigger, more general, audience.

I think I’ll say something like this:

The reason you can have a heart attack even after a normal stress test is that it isn’t necessarily the biggest blockages that cause heart attacks.

Big blockages, or plaques, don’t develop overnight. They take a while, and are more likely to either be silent (if other blood vessels take over the blood flow, like when commuters start to choose the side streets because the highway gets too congested) or to cause what we call stable angina.

Stable angina is chest pain after a certain work load, say two flights of stairs but not one.

Big blockages don’t always cause people to have chest pain if they push themselves too hard; diabetics, for example, often don’t feel pain when the heart is suffering lack of oxygen from its diminishing blood supply, because diabetics can have all kinds of nerve damage, not just in their feet.

Medium sized blockages, say 30-50 percent ones, are the scariest ones, because they may not limit blood flow enough to cause EKG changes or any visible decrease in the radioactive glow we measure in a nuclear stress test.

But 85% of all heart attacks happen as a result of plaque rupture. The wall of the plaque breaks and the “gooey stuff”, cholesterol and other lipid particles, oozes out into the blood stream and a clot forms around it. That’s why we give “clot busters”, fast acting blood thinners, to people who are teeter-tottering on a heart attack. This is what we call Acute Coronary Syndrome.

A couple of decades ago, doctors first gave Lipitor to people with Acute Coronary Syndrome and their pain went away. Lowering cholesterol doesn’t happen that quickly, so what was that all about? More on that in a bit.

Of course, big blockages can rupture, but they are more likely to cause warning symptoms before that happens, while the smaller ones are undetectable unless you do a heart catheterization on everybody.

(CT scans can be used to look for calcified plaque, but the non-calcified, softer plaque might actually be more dangerous.)

So, let me come back to he smaller blockages.

The first thing to make clear is that our arteries are not metal pipes, or even plastic tubes. they are living tissue. And just like our skin renews itself every thirty days or so, our arteries are undergoing all kinds of repair and renewal.

One important aspect of how healthy our arteries are is whether there is inflammation, and we are talking coronary arteries here, but the same thing holds true for the blood vessels to our feet and our brains, too.

When there is inflammation in, say a knee or on the skin, there is redness and swelling and all kinds of chemical reactions that work great if you need to heal broken bones or open wounds. But that kind of reaction can also lead to unwanted bone spurs, thick and peeling skin or, in our arteries, plaque formation.

And sure enough, people with inflammation, be it rheumatoid arthritis or chronic gum infections, on average have more plaque and more heart attacks than you would expect from looking at just the classic list of risk factors, like blood pressure and cholesterol.

Another alarming tidbit here is that some foods cause inflammation, like sugars and refined carbohydrates, while other foods like fish and olive oil reduce it.

In addition to lipid blood testing for determining heart attack risk, we sometimes use blood tests we call “inflammatory markers” (one of them is CRP, or C-Reactive Protein) to decide who should take drugs to lower their heart attack risk.

And this is where Lipitor, now generic atorvastatin, comes in.

It was one of many “statin” drugs developed for lowering harmful LDL cholesterol. It also lowers inflammatory markers in the blood, and as we found out after years of study, it decreases, and in high doses it can even reverse, plaque buildup in the neck arteries as measured by ultrasound, and it can reduce heart attack and stroke risk by 30-50%.

There are other, non-statin drugs (like Zetia), that lower cholesterol and inflammatory markers, but have nowhere near the impact on heart attack risk that the statins have.

So what’s going on?

We now know that Lipitor and the other statins actually do five things:

1) THEY LOWER CHOLESTEROL AND LDL, and that means something but is probably not their main action.

2) THEY MAKE THE PLAQUE WALL LESS BRITTLE, LESS LIKELY TO RUPTURE.

3) THEY PREVENT PLAQUE BUILDUP AND CAN SHRINK EXISTING PLAQUE.

4) THEY HAVE ANTI-CLOTTING PROPERTIES THAT ARE DIFFERENT FROM THE WAY ASPIRIN WORKS.

5) THEY RELAX THE LITTLE MUSCLES IN THE WALLS OF OUR ARTERIES THAT CAN CAUSE “CORONARY SPASM”.

The second through fifth of these mechanisms are well known by now, but we can’t measure them, so people still spend a lot of attention on the numbers that we can measure.

And speaking of measures: In 2013 the American Heart Association and the American College of Cardiology issued a new lipid guideline, with an update added this past year.

Instead of dividing people into just high, medium or low risk for heart disease, the new guideline has a calculator that lets you figure out somebody’s ten year risk. You can then compare this to the best case scenario, and also see what the impact would be of treating blood pressure, quitting smoking or taking Lipitor.

Now, I don’t mean to be overly enthusiastic about Lipitor. It can have unwanted side effects, from brain fog to rising blood sugars to muscle aches. But I am enthusiastic about how much better we understand how heart disease develops.

And I am also excited about what other research has shown: Our diet and lifestyle can address the same five mechanisms of action that Lipitor does. There is more and more proof that avoiding junk food and soda, following a plant based OR a Paleo OR Mediterranean diet, being physically active, sleeping well, managing stress and so on, can have the same impact and reduce a person’s heart attack risk by half.

I’m sure there will be reasons to ad-lib, answer questions, go in depth or off on tangents, but this is the framework I’ll start out with.


I just realized none of the posts show on an iPad or a computer, but they do show on an iPhone. WordPress is working on this. In the meantime, please visit my Substack.


Osler said “Listen to your patient, he is telling you the diagnosis”. Duvefelt says “Listen to your patient, he is telling you what kind of doctor he needs you to be”.


BOOKS BY HANS DUVEFELT, MD

CONDITIONS, Chapter 1: An Old, New Diagnosis

Top 25 Doctor Blogs Award

Doctor Blogs

Enter your email address to subscribe to this blog and receive notifications of new posts by email.

Mailbox

contact @ acountrydoctorwrites.com
Bookmark and Share
© A Country Doctor Writes, LLC 2008-2022 Unauthorized use and/or duplication of this material without express and written permission is strictly prohibited. Excerpts and links may be used, provided that full and clear credit is given.


