Archive for the 'Progress Notes' Category


A Country Doctor Reads: February 2, 2019

McDonaldization of Chronic Pain Therapy (and All of Primary Care?) in the USA – BMJ

A recent Open-Access piece in the British Medical Journal about what they called the “McDonaldization of Chronic Pain Therapy” made me think that this phenomenon, which I hadn’t heard called that before, was certainly present in Primary Care, too. I have sometimes found myself saying, or at least thinking, that 15 minute medicine is more like McDonald’s than fancy restaurants.

The article lists four dimensions of what they have termed McDonaldization:

Number four stopped me cold – this is Healthcare today. The BMJ article states:

“The fourth dimension of McDonaldization is control—control of employees, of the system and of consumers. McDonald’s uses a controlled system, comprising a combination of humans, computers and cooking technologies to serve ‘precut and preprepared food’ to hungry customers, eager for their salty fix. This system minimises the need for human creativity and effort on the part of both employee and consumer. In the context of chronic pain management, OxyContin worked very similarly and thus produced a strange control over both doctor and patient. Physicians no longer had to parse out what exactly the cause(s) of a patient’s pain was and what therapies they might benefit from, but rather, now had the option of giving one drug to keep it all at bay.

Purdue Pharma’s aggressive and patently false advertising of the safety of the drug positioned OxyContin as the most rational and efficient choice a physician could make in treating a patient in pain. This only served to benefit the controlled McDonaldized system Purdue Pharma was helping construct, because people—physicians included—are ‘the great source of uncertainty, unpredictability and inefficiency in any rationalizing system’.

The responsibility of treating patients with chronic pain often falls to primary care physicians, and as such, they were Purdue Pharma’s prime target in expanding the ‘OxyContin prescribing base’. With the increasing demands of medical McDonaldization, one of the highest burnout rates of all physician specialties, and the shortage of primary care physicians ever growing, they were understandably susceptible to believing the promises of the drug. Furthermore, these physicians were already fighting multiple American epidemics, like pre-diabetes and hypertension (for which McDonald’s itself happens to be a significant contributor). So, if there was a quick, effective treatment for another complex finding—pain—available, then there was little desire or opportunity to take the time to question the legitimacy of Purdue’s claims. Thus, they prescribed the drugs liberally, as they were instructed to at their Purdue-funded educational conferences.”

Yours truly wrote a little while ago about the downside of even using the word “treatment” for chronic conditions, instead thinking “guidance” better describes what we ought to be providing.

“Treatment”, the second part of the traditional duad, is too simplistic a notion, only useful for lancing boils and prescribing penicillin for strep throat. Most diseases are multifaceted and most patients have several health and disease considerations. Most diseases are also chronic, even ones we thought of as rapidly terminal earlier in our own lifetime, like HIV and an increasing number of cancers.

The physician’s role is not a knee jerk intervention, it is informing and educating the patient and helping each patient choose a plan of action that is right for them.

Primary Care does what Google can’t, it applies knowledge of the patient and of the relative importance of medical facts and factoids and offers guidance in the sense of ranking options.

https://acountrydoctorwrites.blog/2018/10/08/fundamentals-of-medicine-diagnosis-and-guidance-not-just-treatment/

https://fmch.bmj.com/content/7/1/e000069


Does Anybody REALLY Want to Fix Physician Burnout?

In my inbox the other day was an AMA update that was mostly about burnout:
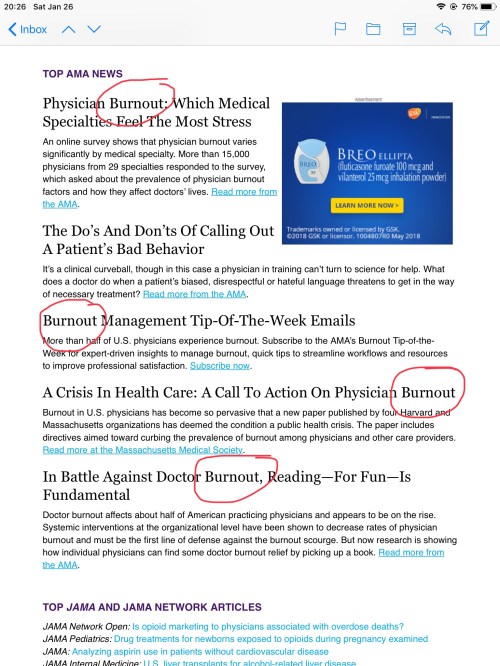
http://www.massmed.org/News-and-Publications/MMS-News-Releases/Physician-Burnout-Report-2018/

This is getting out of hand. We have two crises converging to soon cripple and bankrupt our health care system and quite possibly our entire economy:

1) An aging population and people of all ages that are increasingly affected by chronic diseases that were rare a generation ago.

2) A burned-out, disillusioned and hamstrung medical profession, unable to do anything in their allotted 15 minute visits about the lifestyle-dependent epidemics beyond prescribing $400-$1,000 a month drugs that allow the disease snowball to keep rolling and growing, albeit at a somewhat slower rate.

I recently wrote about burnout:

“Put simply: If anybody wants to define and manage our work for us instead of letting us do it, they become responsible for the outcomes if we aren’t given the time or the tools we, as the ones who went to school, know we need.

The cure for physician burnout is simple: Listen to us when we say what we need in order to do our best. We didn’t spend all this time and energy so we could collect our salaries and goof off.

Most of us still have a professional mindset. We want to do a good job and we know how to do it. Let us.”

https://acountrydoctorwrites.blog/2018/12/20/the-root-cause-of-physician-burnout-neither-professionals-nor-skilled-workers/

BUT, as one commenter wrote:

“Well said, and so true. But the solution is NOT ‘simple”, because THEY will never listen to us. The difficult, but only realistic solution is to be independent…”

So, we need some honest answers and some new paradigms here:

What is disease?

What is public health?

What do we need doctors to do if there are so few of them?

Does every “stakeholder” benefit if people get healthier? Or do some profit from continuing worsening of our nation’s health?

That last point is obviously rhetorical. What kind of health care system can reconcile when insurance companies and pharmaceutical companies actually profit from people being sicker?

Checking Boxes

I pay $500 per year for UpToDate, the online reference that helps me stay current on diagnostic criteria and best treatment options for most diseases I might run into in my practice. They also have a rich library of patient information, which I often print out during office visits.

I don’t get any “credit” for doing that, but I do if I print the, often paltry, patient handouts built into my EMR. That was how the rules governing meaningful use of subsidized computer technology for medical offices were written.

If I describe in great detail in my office note how I motivated a patient to quit smoking but forgot to also check the box that smoking cessation education was provided, I look like a negligent doctor. My expensive EMR can’t extract that information from the text. Google, from my mobile device, can translate between languages and manages to send me ads based on words in my web searches.

When I do a diabetic foot exam, it doesn’t count for my quality metrics if I freetext it; I must use the right boxes. If I do it diligently on my iPad in eClinicalWorks, one of my EMRs, even if I use the clickboxes, it doesn’t carry over to the flowsheet or my report card.

Not only are these things annoying and part of the mounting overall frustrations of being a doctor, or PA/Nurse Practitioner, today. They are also misguided; I may document a foot exam or provide a disease specific handout, but then what?

Our primitive technology can’t automatically do anything more. Did the printed information change my patient’s behavior? Did the foot exam reveal diabetic complications, and did I do anything about that? Did my smoking cessation advice (CPT code 99406) produce results? Or did the patient quit on her own because her sister got lung cancer?

More and more, I am thinking we, as providers, are measured too much for the wrong things.

I also think that, more and more, we are expected to do the wrong things.

My diabetic patient may see a well qualified podiatrist, who spends a great deal of time examining and treating my patient’s feet, but I am the only one who can prescribe the diabetic shoes. How detailed does my foot exam have to be for that prescription to count? Not very, mostly clicking the designated box.

I don’t double check the retina specialist’s work examining and injecting my diabetic patient’s eyes, now, do I? I am only charged with documenting that my diabetic patient sees the eye doctor. I wonder why Medicare needs me to tell hem that when they are presumably paying big money for that to happen?

In our fifteen minute world, wouldn’t it be better if I had time to read the podiatrist and eye doctor reports and use them to help motivate my patient to eat differently and exercise more? Instead of:

Have you seen the eye doctor? Check.

Have you seen the podiatrist? Good, let me check your feet real quick so I can say I did it and get you the shoes he wanted you to have…Check.

And do you know smoking is bad for you? Check.

Do you know too many carb calories raise blood sugars and cause weight gain? Check.

You don’t drink too much, do you? Check.

Not too depressed this time of year? Check.

Did you get your flu shot, colonoscopy and Pap smear? Check.

And what about hepatitis C, domestic violence and making out those Advance Directives? Check.

Makes me feel I’m a great doctor. Or does it?

There is another dimension of Medicine, invisible to those who measure us, but it is the only one our patients see.

Unavailable Antidotes

Last week I had a patient with mild kidney disease and a high potassium. I thought that would be easy to take care of. We called around to all the pharmacies from Bangor to Ellsworth to Belfast and nobody had Kayexalate, the time-tested antidote, in stock.

It happened to be on a Tuesday night with my Suboxone group starting at 5 o’clock. The patient had been there since 4, his labs were available by 4:30.

It was 4:45 and we were almost done calling around to pharmacies. I had Autumn, my medical assistant, make some of the calls. 15 minutes left before clinic with 14 patients to see in 90 minutes (we pull them out from group therapy to check in and renew their scripts). And I had a new patient, an internal transfer but still new to me, with multiple medical problems to see before clinic.

I did what I hardly ever do: I asked Autumn to call the emergency room on my behalf and tell them that we had no choice but to send the patient over. We faxed records and lab reports and I moved on.

The ER doctor’s report was scathing. He clearly thought I had dumped on him. He didn’t do what I had thought he might do:

I hadn’t done it since I stopped doing hospital medicine a generation ago but I know you could hydrate him to help his mild acute kidney injury and coadminister glucose and insulin to lower the potassium at the same time.

Instead, the emergency room doctor gave him Kayexalate, because the hospital had it in stock. He probably didn’t know that wasn’t an option for us. I looked like an idiot to him, but that often happens in primary care.

I had gotten over my frustration and embarrassment when, this week, I had a patient on warfarin with a supratherapeutic INR and no active bleeding. I’ve never been terribly nervous about those situations but this was a high number and Up-To-Date suggested vitamin K, orally because it works faster than injectable, while obviously holding the warfarin. So, guess what, we called every pharmacy from Bangor to Ellsworth to Belfast and nobody had vitamin K in stock. The Natural Living Center in Bangor had a very low potency supplement where maybe 50 pills would be enough of a dose to make a difference.

Oune of the hospital pharmacists was available to talk to me and explained that a small bottle of vitamin K in the potency required to reverse warfarin costs about $1,000 and neither hospitals nor pharmacies want to stock them because they will lose so much money if the drug expires. What the hospitals do instead is compound an oral form from the injectable that is still expensive but less so. But a hospital can’t sell or administer to an outpatient whose primary care physician does not have privileges at that hospital. I technically have privileges at Cary Medical Center in Caribou, but that’s 200 miles north.

So this was a judgment call: Send the patient to the emergency room so she can incur the emergency room fee and have them give her an oral medication that may or may not make a difference since she had no active bleeding. Or I could bubble wrap her for a couple of days while the warfarin effect wore off.

Today, in Van Buren, I called the small local Rexall (a historical U.S. pharmacy name) and chatted with the owner, John Hebert. He has Kayexalate in stock. This is in a town of 2,000 people. From Bangor to Ellsworth to Belfast I imagine there are 100,000 people. They don’t have outpatient access to this drug.

It’s a sad situation when potentially life-saving medications are unavailable because pharmacies don’t want to risk having them expire and go on unsold. We have automatic defibrillators in schools and shopping malls, why not some basic antidotes available, maybe even subsidized, in strategically located pharmacies?

P.S. Hebert’s is about to open a pharmacy in Bangor within the next few weeks and John has promised to stock Kayexalate there, too. And he delivers to a large geographic area…

A Spot-On Analogy

The young woman was only slightly overweight, with a BMI of 28, but she seemed really wound up about her need for me to continue the phentermine her previous doctor out of state had started her on. She volunteered that her BMI was only 29 when she started.

She was a walk-in patient, not a regular, and we didn’t have any records on her, except I was able to verify her prescriptions on the multi-state Prescription Monitoring Program website. I told her it was incredibly easy to lose weight if you really want to, “just don’t eat any refined carbs”, and cited my own example as a recovering vegetarian.

She almost broke into tears.

“With your weight, you don’t even have to be all that radical to get your BMI down under 25”, I tried to reassure her. She did not seem reassured.

I decided to try some analogies.

“Taking diet pills with a BMI of 28 or 29 is like asking for ADHD medication just so you can stay up all night and study for a final exam; it’s not a case of a lifelong, debilitating problem.”

She burst into tears.

“They do help me keep track of my life, I’m so disorganized and so distracted. I flunked out of college, I can’t keep a job…”

“So you think you have ADHD?”

“Yes, and PTSD and anxiety.”

“Well, then, let’s deal with that! I’ve got Behavioral Health Staff right here. On Saturdays, too.”

She stopped crying. I looked at the clinic schedule. My psychologist had a no-show.

“I can introduce you to my psychologist, who can help figure out your diagnosis. Would you like to meet him?

“Sure”, she said and straightened up in her chair.

“You wait right here and I’ll be back in a few minutes.”

I made the introduction, mentioned that I have collaborated with Dr. Brandt for 25 years, and said:

“I’ll refill the phentermine for one month only, and you guys figure out what’s the real problem with your attention. Then, when you see your new primary care provider, you’ll be able to go over what you and Dr. Brandt have found out and go from there. Deal?”

“Deal”, she said, and added “Thank you. I was almost ready to walk out.”

“Just be straight with us. We’ll work with you”, I said and excused myself.

There were three more walk-ins waiting to be seen.

I love my job. And I love working in an integrated practice.

Outlook and EMRs: Culture Clash in the Medical Office

I have many equally important administrative and clinical duties, but I miss many more meetings than patient appointments. The reason for this is simple: Non-clinical activities are scheduled by non-clinical people in Microsoft Outlook and patient appointments are scheduled in our EMR.

No-showing for a patient appointment is extremely bad patient care, and I go where the EMR tells me to go.

Outlook can send instantaneous, simultaneous invites to hoards of people, who with one screen tap or click can accept and populate their schedules years in advance.

The EMR requires specially trained and authorized people to custom create blocks of various types which may show up in one (grid) view but not in another (list) view.

This is a small, but telling example of how an activity that even the most basically computer literate person handles automatically in the business world requires special skill and privileges in a modern EMR.

Non-clinical coworkers are still puzzled by my seemingly erratic meeting attendance, and they give me blank stares when I suggest they stop using Outlook and make the EMR their appointment book and message hub. They’re no fools; they know how clunky my technology is.

And (I’m on a roll now), compare EMR messages with email: If a clinical message in my EMR has various new timestamps and comments added to it, it doesn’t move to the top the way emails do; it stays in the order it was created, so while I never miss a patient appointment, I do miss new information in patient communications.

Why does my EMR not work like modern office computer programs? It’s a rhetorical question we all know the answer to: Proprietary functionalities of their software with lack of interoperability is a cornerstone of the business strategy of EMR vendors; profits to be made as long as customers stay with the product. And the more expensive and complex it would be to migrate data and retrain people, the surer those ongoing profits are.


I just realized none of the posts show on an iPad or a computer, but they do show on an iPhone. WordPress is working on this. In the meantime, please visit my Substack.


Osler said “Listen to your patient, he is telling you the diagnosis”. Duvefelt says “Listen to your patient, he is telling you what kind of doctor he needs you to be”.


BOOKS BY HANS DUVEFELT, MD

CONDITIONS, Chapter 1: An Old, New Diagnosis

Top 25 Doctor Blogs Award

Doctor Blogs

Enter your email address to subscribe to this blog and receive notifications of new posts by email.

Mailbox

contact @ acountrydoctorwrites.com
Bookmark and Share
© A Country Doctor Writes, LLC 2008-2022 Unauthorized use and/or duplication of this material without express and written permission is strictly prohibited. Excerpts and links may be used, provided that full and clear credit is given.


