Archive Page 107

A Wonder Drug of Ill Repute

If I could only have one drug in my pharmacopeia, what would it be?

An antibiotic? A pain reliever? A happy pill? Keep guessing…

During my Saturday clinic I saw a man I had done a physical on two weeks before. He told me he had suffered from daily headaches for several years and was popping over the counter medications just about daily to no avail; he clearly had developed rebound headaches on top of his frequent migraines. In today’s appointment he announced he had been headache free for nearly a week from the ten day prescription I had given him.

I also saw a woman with hives from head to toe. I prescribed for her with absolute confidence that her symptoms would go away.

Another patient with what the rheumatologist called inflammatory polyarthritis was not doing well on methotrexate, but told me that while she was on prednisone before that, she felt normal.

A few days before I saw a sciatica patient whose leg pain had completely resolved within a week of his first visit with me.

The day before that I prescribed it for a woman with a flare up of multiple sclerosis.

Prednisone is truly a wonder drug. It treats allergies, sciatica, gout, eczema, intractable headaches, rheumatoid arthritis, inflammatory bowel disease, asthma and COPD exacerbations, chronic lymphocytic leukemia (at least when I was a medical student), cancer related hypercalcemia and a multitude of other conditions.

It is about as old as I am, and neither of us has many undiscovered secrets left.

In the case of prednisone, that is very comforting to me.

Younger doctors are more afraid of it than I am. I have seen a colleague with arthritis die from a newer medication due to pneumonia and sepsis. I worry about the way many of these newer agents can cause problems very suddenly; prednisone is a bit more predictable.

Years ago I had a British reader question my use of prednisone for acute gout. It is my go-to, better tolerated than colchicine and safer on stomach and kidneys than indomethacin.

It is amazing what steroids do, not only to rheumatological conditions but also to our pain perception. I liken their effect to the instant ability people have in times of crisis to exert more effort than any other time and never notice pain or weakness; it can give us the sudden ability to run faster than ever before, lift heavy objects that pin down an accident victim and so on.

In some arenas it has had a renaissance: I learned in school that it decreases our ability to fight acute infections, but now it improves survival in septic shock.

The problem is its side effects with long term use, but its versatility in acute care is amazing and I do think it would be the one drug, if had to pick a single one, in my extreme survival kit.

But, may I please have one or two more?
A Country Doctor Reads: March 23, 2019

Health Insurer Profits From Your Death, Life Insurer Profits From Your Survival – WSJ

If you get sick and die quickly your health insurance doesn’t have to pay out a lot of money. They lose money by providing you expensive cancer treatment for example. Your life insurance on the other hand wants you to stay alive long as possible so they don’t have to pay out the death benefit. In a thought-provoking article the Wall Street Journal points out that this opens doors to access to expensive treatments for cancer and other serious illnesses.

www.wsj.com/articles/health-cares-killer-app-life-insurance-11553122054

……..

From Ancient Greece to Yours Truly to NYT: Is Pain a Sensation or an Emotion?

We seem to be catching up with the old Greek philosophers in acknowledging that pain isn’t an objective sensation, but more of a subjective, emotional experience. Here’s a nice piece from The New York Times:

www.nytimes.com/2019/03/16/opinion/sunday/pain-opioids.html

Looks like NYT has been reading my blog; I pointed this out March 9 😎:

Plato and Aristotle didn’t include pain as one of the senses, but described it as an emotion. The word “pain” is derived from Poine or Poena, the Greek goddess of revenge and the Roman spirit of punishment. Her name is also the origin of the word penalty.

https://acountrydoctorwrites.blog/2019/03/09/a-country-doctor-reads-march-9-2019/

.. and I wrote about it in 2013:

https://acountrydoctorwrites.blog/2013/12/09/pain-and-suffering/

…………

Priests, Providers, and Protectors: The Three Faces of the Physician – Psychiatric Times

I have a soft spot for the comparison of physicians and priests (See my 2009 post “Thank You, Father“). And, like many doctors, I’m not crazy about the term “provider”.

Psychiatric Times has a very nice essay on the topic by their Emeritus editor, Ronald W. Pies, MD, where he proposes a role between the extremes of Priest and Provider:

..

“I believe there is a “third way” of viewing the role of the physician—one that neither elevates the physician to the exalted (grandiose?) position of “priest” nor demotes us to the level of mere “providers.” In the role I call the Protector, the physician’s chief obligation is the safeguarding of the patient’s physical, emotional, and spiritual well-being.”

Between the extremes of priest and provider lies the healing heart of the physician.
— Read on www.psychiatrictimes.com/couch-crisis/priests-providers-and-protectors-three-faces-physician

The Power of Focus

I keep thinking about the dichotomy between covering a lot of ground and getting to the point.

The other day I saw my bosses at one of my clinics stop in their tracks when I suggested that a lot of the things we are measured on as physicians could be turned into standing orders and simply get shifted off my plate. I have just created a letter that anybody can send on my behalf to any patient of mine who hasn’t been screened for colon cancer; it’ll look like I sent it, which is fine, because I support it, but I shouldn’t have to crowd my glorious fifteen minutes with that too in addition to the diabetes and depression and whatever else I need to address.

I seriously believe that doctors have somehow been excluded from the theory of working to the top of your license. And that’s a shame; I’ll gladly lend my name to colon cancer screening, immunizations, diet and exercise and other public health programs.

But, and I’ll probably insult some folks (again): You don’t need a medical degree and decades of experience to carry out no-brainers like that.

I want my training and experience put to a different use: Seeng what matters in a tangled mess of symptoms or data, making interconnected value and probability judgements and disregarding a patient’s formal response if their demeanor or body language suggests that their answers are incongruent. (What percentage of suicidal patients answer that question truthfully?)

I often find myself abdicating from deciding if a late patient can still be seen or if one person needs to go ahead of another: I’m too focused on something else.

It is my ability to hyperfocus that lets me deal with a diagnostic dilemma in short order. Don’t ask me to also direct traffic or upsell with unrelated health maintenance gaps in care.

When my patients say “he really listens”, it means “he focuses” and “he’s not all over the place”.

I don’t think you can have it both ways.

Pay me to focus and pay somebody else to do he housekeeping.

I’m an artist, a problem solver, not an accountant.

No Information Exchange, Major Diagnostic Delay

I’ve known Pat McCann for many years. He carries a diagnosis of COPD and has a preventative and a rescue inhaler, but he has never really had any serious flare-ups.

He fell and broke his hip. Then he went to skilled rehab, one of a half dozen near Cityside Hospital. His stay turned longer than expected because he fell, luckily didn’t break anything, but had to go back to the hospital because he hit his head and needed to be observed for a small subdural hematoma.

I saw him late Friday afternoon for a Hospital Followup visit. Medicare pays us handsomely for such Transition of Care visits (CPT 99495 or 99496) when a Care coordinator reaches out by phone, does a medication reconciliation, makes sure what followup tests are needed, if the patients understand their instructions and so on.

In this case, we had reams of printouts from the two hospitalizations, but we only had a medication list from the rehab facility. Pat’s regular boarding home had all kinds of questions about all his nebulizers, his oxygen orders and so on. We never did get anything from the nursing home, so “Continue the nursing home orders until we see him”, was all we could tell them, as we had nothing to go on.

So, 4 pm Friday Pat shows up, in a wheelchair, tied to an oxygen tank set at 3 liters per minute. He is coughing. He tells me he is raising phlegm, green and brown. His lungs have crackles and wheezes on both sides. I get a normal blood count and a chest X-ray that shows double pneumonia.

I know what happened. I used to be Medical Director at a rehab facility.

Because he carried a diagnosis of COPD and was on a maintenance inhaler, and because he ended up coughing and desaturating, it is safe to assume a nurse acted on standing orders to administer oxygen to COPD patients to keep levels above 90%. It is also likely that the inhalers were switched to nebulizers because his symptoms weren’t controlled.

It is equally likely that no medical provider assessed him at that time, and only responded to incoming faxes from the rehab facility. There’s only so much time for sick visits when you round at the nursing home, which is not every day.

It is also absolutely certain that the rehab facility had no access to my records, and even if they did, would not have had the available time to go through them to see that he he’d never ever had a serious COPD exacerbation before.

It is also a cold hard fact that it is easier and less expensive for the rehab facility to administer oxygen and nebulizers than to put him in a wheelchair van and send him, with staff, across town to the hospital for a chest X-ray to check for pneumonia.

I sent Pat home with prescriptions for prednisone and antibiotics and a few words of encouragement about hopefully getting him off the oxygen soon.

I think we could do better…

A Country Doctor Reads: March 16, 2019

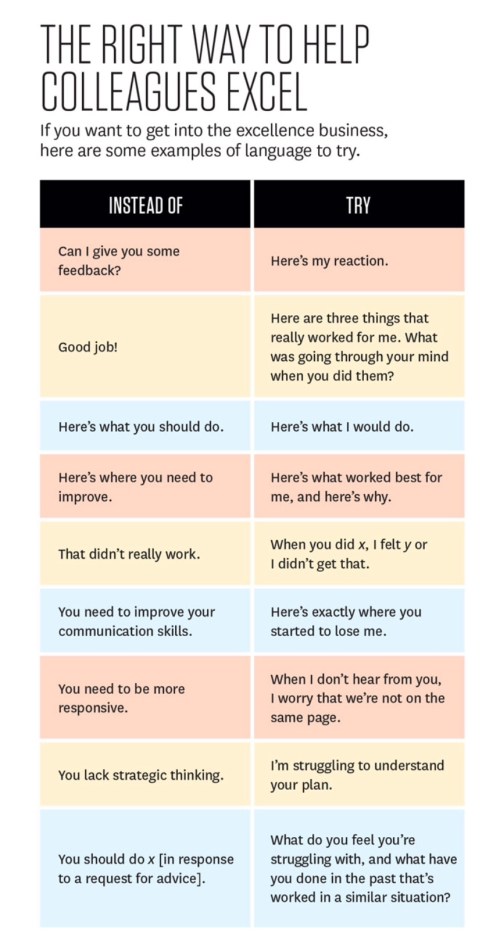
The Right Way to Help Colleagues Excel – Harvard Business Review

Having just completed annual provider reviews, this sobering and thought-provoking article in the Harvard business review caught my attention, partly because of how you could give better feedback but also because in the business world they apparently don’t have to stick to a formula or protocol like we are supposed to do in medicine. I guess they want people who can think for themselves??

”How to give people feedback is one of the hottest topics in business today. The arguments for radical candor and unfurnished and pervasive transparency have a swagger to them …… But at it best, this fetish with feedback is good only for correcting mistakes-in the rare cases where the right steps are known and can be evaluated objectively and at worst it’s toxic because what we want from our people-and from ourselves-it is not, for the most part tidy adherence to a procedure agreed-upon in advance or, for that matter, the ability to expose one another’s flaws. It’s that people contribute their own unique and growing talents to a common good, when that good is ever evolving, when we are, for all the right reasons, making it up as we go along. Feedback has nothing to offer to that.”

https://hbr.org/product/harvard-business-review-march-april-2019/BR1902-MAG-ENG

*

Beyond the Borderline – The Lancet Psychiatry

I had another Saturday wrap-up with my Behavioral Health Director last week, and I asked if he thought a mutual patient had Borderline Personality Disorder. He didn’t think so, because he doesn’t believe in it. I still can’t quite wrap my head around it, so I guess I don’t believe in it either. Looking for an update, I found this in The Lancet Psychiatry:

“Borderline personality disorder is not so much a diagnosis as it is a liminal state. Individuals to whom the label applies exist between mental illness and mental health, between experiencing an acute condition and a chronic condition, and between being highly visible to clinicians, yet invisible to major epidemiological projects such as the Global Burden of Disease. The diagnostic criteria for personality disorder fall between the objective descriptions expected of medical manuals, and value judgements based on received opinion. DSM-5, for example, includes diagnostic criteria of inappropriate, intense anger. It is hard to conceptualise anger that is not intense in nature; and as artist, writer, and mental health trainer Rachel Rowan Olive asks, “Who decides when anger is appropriate?” The past few years have seen events such as the revelations regarding child abuse in the Catholic Church and the global #MeToo movement, which have given survivors of exploitation and injustice platforms with which to share their stories and experiences. Their anger would perhaps have been considered inappropriate and intense only a decade or so ago, by societies in denial about the existence and the extent of their problems. Despite these advances, it is still possible that people with a history of abuse might suffer twice: first from the abuse itself, and second from having their resulting emotional response pathologised.”

https://www.thelancet.com/journals/lanpsy/article/PIIS2215-0366(19)30051-3/fulltext


I just realized none of the posts show on an iPad or a computer, but they do show on an iPhone. WordPress is working on this. In the meantime, please visit my Substack.


Osler said “Listen to your patient, he is telling you the diagnosis”. Duvefelt says “Listen to your patient, he is telling you what kind of doctor he needs you to be”.


BOOKS BY HANS DUVEFELT, MD

CONDITIONS, Chapter 1: An Old, New Diagnosis

Top 25 Doctor Blogs Award

Doctor Blogs

Enter your email address to subscribe to this blog and receive notifications of new posts by email.

Mailbox

contact @ acountrydoctorwrites.com
Bookmark and Share
© A Country Doctor Writes, LLC 2008-2022 Unauthorized use and/or duplication of this material without express and written permission is strictly prohibited. Excerpts and links may be used, provided that full and clear credit is given.


