Archive for the 'Progress Notes' Category


A Country Doctor Practices Telemedicine

Walking gingerly, one small step at a time like an old man, I slowly made my way down our icy driveway to the mailbox this morning. The cold wind circled around my neck and the sleet pounded against my cheeks. March was surely coming in like a lion here in the Northeast.

Inside the black metal mailbox were the usual bills and journals, but also a small post card. I brought it closer to try to read it through my wet eyeglasses. It was from a company looking for primary care physicians for telemedicine services.

Telemedicine is an integral part of rural health care. When an accident victim has a CT scan of the brain or cervical spine in the middle of the night, a radiologist in a different time zone reads the images while our own radiologist gets his well-deserved sleep. The specialists who fly or drive here to do consultations sometimes use the hospital’s teleconferencing capabilities for virtual follow-up appointments. We even have telepsychiatry with doctors from Boston and the southern parts of our state.

“Telemedicine for primary care doctors”, I thought as I inched my way up the slippery driveway in the bitter cold sleet storm. I imagined myself in my slippers and cardigan, comfortably doing telephone consultations by the fire. I saw myself poolside in my swim trunks, sipping from one of those parasol drinks, making money on the phone while working on my tan.

I have already done some telemedicine. Last weekend my daughter sent me a picture on my cell phone with the question what kind of rash my grandson had. It was a classic case of erythema annulare. He happened to have an appointment with his doctor a few days later, and I understand the diagnosis was confirmed in person then.

Then I remembered I had been less successful a few weeks before that when my granddaughter had a host of symptoms, including a fever and, as my daughter added: “She won’t eat”. It all sounded pretty viral to me, so I gave the usual advice. A couple of days later, I found out the child had a flaming case of strep throat.

I asked sheepishly “How sore was her throat?”

“Real bad, didn’t I say that?” My daughter seemed puzzled.

“I only heard that she wouldn’t eat”, I said.

“Yeah, because her throat was so sore”, she answered.

A visual would definitely have helped there. If it was that hard to diagnose my own granddaughter over the phone, I can imagine the challenge of trying to do more than the simplest triage over the phone with a complete stranger who is paying for the call.

I kicked the snow off my boots and entered the glassed-in front porch. My eyeglasses were frosted on the outside and fogged up instantly. I took my boots off, put the journals on my reading pile and the bills on the staircase to the upstairs. I turned the post card over one more time, shrugged to myself, put it in the kitchen trash and poured myself another cup of hot coffee.
Jumping to Conclusions

Muffy Wahl slipped backwards on her icy porch and landed on her right hip. Bruised and sore, she took it easy for a few days but she still went to her exercise class the following Thursday. The petite sixty-three year old was determined not to let a silly little fall set her back, and she did her jumping jacks to the loud, fast music with more determination than usual. She could barely drive herself home afterwards.

After dinner Thursday night she didn’t know what to do with herself; she shifted her weight back and forth, but the pain was just as bad no matter how she positioned herself. Getting ready for bed she noticed the bruises were bigger and now reached around to her groin.

Even flat on her back she was in pain. It was a constant, relentless, nauseating pain unlike anything she had experienced before.

Friday morning she got a call from her twin sister, Mary, who had just been admitted to the hospital with a hip fracture. Muffy promised to go and see her, even though it meant a twenty-mile drive. She took some ibuprofen and drove off to see her sister.

After the two women had visited for a while, Mary noticed Muffy’s pained expression as she shifted her weight in her chair. Mary suggested that Muffy get herself checked out downstairs in the emergency room. Muffy hesitated, still thinking it was just a bad bruise. Besides, she had never had any dealings with St Bartholomew’s Hospital; she always went to Cityside.

Mary insisted, and soon Muffy was downstairs, wearing a hospital gown and being wheeled into x-ray.

“The x-rays were normal and they said it was just a bad bruise”, Muffy told me Monday afternoon in the office “Then they gave me a shot for pain that wouldn’t make me tired. I drove myself home later on.”

“And then…” I asked.

“I noticed the welts Saturday morning. I’ve been in agony all weekend.”

“Welts?”

“Yes, I thought it might have been an allergic reaction to the shot they gave me, but they were only around my right hip.”

“Let me see”, I said.

She exposed the skin around her right hip. There were bruises, red blotches, and the unmistakable blisters of Herpes Zoster – shingles.

“This is shingles. Did anyone look at your skin?” I asked.

“No, they checked how my hip moved and took the x-rays through the hospital gown”, she answered.

Today’s Masterpiece

“Make every day your masterpiece.”

             Coach John Wooden

“…to do the day’s work well and not to bother about tomorrow. You may say that is not a satisfactory ideal. It is; and there is not one which the student can carry with him into practice with greater effect. To it more than anything else I owe whatever success I have had — to this power of settling down to the day’s work and trying to do it well to the best of my ability, and letting the future take care of itself.” 

William Osler


Whether you are America’s most legendary basketball coach, the father of modern medicine or a busy primary care doctor in a remote rural area, there is only one right way to get through each day. In the practice of medicine with its daily ration of two dozen fellow human beings in some sort of need, we often only have one chance to get it right.

As a young man and newly trained physician, I spent a lot of time thinking about the future. I know I sometimes devoted less attention to the here and now than I should have.

Today I carry with me all kinds of memories of the past; some are useful clinical impressions and life experiences that help me be a better doctor, others are sentimental distractions I need to manage in order to be effective in the present moment.

I am also distracted by the future. The changes in health care we all face have me thinking about how things will be different tomorrow, what new skills I will need and which old ones will be obsolete. I also find myself spending too much time thinking about what’s wrong with health care today and imagining how things ought to be.

Most days we primary care physicians don’t diagnose any rare diseases, and we don’t usually know right away if our efforts will produce any lasting results. We know we are constantly being measured and evaluated by insurance companies, employers and many others – even the pharmaceutical companies track our prescription habits. We strive for quality certificates and worry about satisfaction surveys. We devote increasing time and energy to mastering the new technologies of health care delivery and documentation.

Today I spend more time e-prescribing a new medication for my patient with inoperable sciatica than I do choosing the drug and the dose in the first place. If I don’t specify capsules or tablets, or if I should neglect to put in “by oral route”, which I always thought was obvious with both capsules and tablets, the script won’t go through. I start thinking about what I would like to say to the IT people or how I would change the technology if somebody would just give me the opportunity.

Tonight over dinner Emma asked me one of those questions only she can ask me:

“In your work as a doctor, are you striving to meet your patients’ needs or your own?”

Before I had time to swallow and clear my throat, she continued:

“Because if you’re in it to fill your own needs, you’ll never be happy, since health care is not run by you or any other doctor anymore. If you focus on how things ought to be instead of doing the best for your patient in the reality of the moment, you’ll never be satisfied. If it’s not enough for you to know you did your best for that patient, then you’re in it for the wrong reasons.”

There are days when I clearly see that I made a difference in the life and welfare of a fellow human being because I saw what needed to be done and put my abilities to use. Those are the days I come home and tell Emma that I feel good about being a doctor.

Then there are those days when I talk about what kinds of things stood in my way of being a good doctor – excuses, really, when I think about them. My patients certainly aren’t interested in what my obstacles are. All they want from me is my best effort under the circumstances:

The lab closed early, the computer is malfunctioning, the specialist’s report is missing, the insurance doesn’t cover the medication and the road to the hospital is icy and snow-covered, but the patient is still sick. I am his doctor. Today’s work is today’s work. What more can I do besides make it my masterpiece for today? Isn’t that all I set out to do from the beginning?

“I’m Sorry Mrs. Jones, But You Have Albuminurophobia”

Last week I saw several older patients who were fretting about their mildly reduced kidney function. All of them were women in remarkable health, but each one had at one time or another had a brush with hospital medicine:

Mrs. Allard had a mastectomy five years ago, Mrs. Perlman had an episode of clostridium difficile colitis last year after taking antibiotics for a dental infection, and Mrs. Jones had just finished rehab after a knee replacement. All three women had been labeled as suffering from chronic kidney disease during their hospitalization.

Mrs. Allard was in on Monday. She never fails to ask what her Glomerular Filtration Rate is when she comes in for her visits. Every time I have to reassure her that her numbers are stable. She struggles to believe me when I tell her that her frequent urination is not a warning sign of impending kidney failure.

“GFR is chemistry, bladder spasms are a plumbing problem”, I tell her every time. “They are not related.”

“I don’t want to end up on dialysis and I have read that people with kidney disease are more likely to have heart attacks. My nephrologist tells me that, too. Mrs. Perlman said last Tuesday. Between her quarterly visits with Harold Wesson, the Chief of nephrology at Cityside Hospital, she worries enough to always mention her kidneys when she sees me for other things.

“But, Doctor, I have Stage III kidney disease!” Mrs. Jones said with obvious fear in her voice. It was Thursday afternoon and we really should have been talking about the dark mole on her right thigh.

“That doesn’t mean you’re in any real danger…” I began. She looked suspicious. “In fact, your kidney function two years ago was exactly the same.”

“Are you telling me I had kidney disease already then?” Her eyes widened.

“To the same degree, yes. Do you remember how I asked you to stop taking ibuprofen for your sore knee because it could harm your kidneys?”

“Yes, that’s when you gave me those prescription pain pills.”

“Precisely. I was concerned then that we needed to be kind to your kidneys – that’s pretty much all we do when people have what we call Stage III chronic kidney disease.”

“But you never told me I have kidney disease.”

“I didn’t use the word because I feel it alarms people more than it helps them. We talked about what helps the kidneys and what hurts them; we got you off the ibuprofen, we tightened up your blood pressure control with a new medication and we lowered your cholesterol. All those things help your kidneys work better and last longer.

“But Stage III – I mean, how many stages are there? How close to dialysis am I with Stage III disease?”

I was ready for her question. With all the patients like her I have seen, especially lately, I have put together some articles and teaching materials.

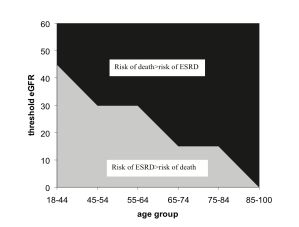
“I have been a doctor since 1979 and I can count on one hand the patients I have cared for that ended up on dialysis or dying from kidney failure. Look at this graph”, I said and pointed to the latest addition to my bulletin board. “You’re 74, and your GFR is 54. This graph shows that at your age, your GFR would have to be somewhere around 15 to make you more likely to die from kidney failure than something else.

She stared at the graph.

“So 54 is actually not a bad GFR?”

“Well, it’s not normal in terms of perfection, but it is very common. Even people who aren’t perfect can live a long and happy life.”

“So you’re saying I shouldn’t worry?”

“Not about your GFR specifically. Remember to be kind to your kidneys, like we have talked about.”

She nodded.

“Now, here’s the bad news”, I explained. “People with even mild kidney disease statistically are more likely to have heart attacks, strokes and other cardiovascular problems.”

She started to raise her eyebrows, and I hurried to continue:

“But, and this is important: I’m not smart enough to know what’s the chicken and what’s the egg. Do they have kidney disease because they have hardening of the arteries everywhere, or does the kidney disease itself cause it to happen?”

I continued:

“So we do the usual things – good diet, cholesterol, blood pressure. And we don’t just focus on the GFR.”

“I can’t help worrying about the numbers”, Mrs. Jones said.

“There’s a name for that”, I told her. “We call it albuminurophobia.”

“Really?”

“Really. There is a medical term for just about everything these days.”

She shook her head.

“Now, about this mole”, I continued…

How to Clicker Train Your Doc

My eyes played a trick on me the other night, or perhaps it was my subconscious. Emma and I were reading by the fire – my nose was in one of my medical journals and she had a stack of animal behavior books next to her while looking intently at the screen of her laptop computer.

As I was reading along I registered the sound of the dogs snoring rhythmically nearby. My eyes glanced over my magazine’s headlines with words like guidelines, accountable care, pay-for-performance, evidence-based and quality.

I had just made the quiet observation that there are innumerable forces that create and use buzzwords like that when trying to tell front-line doctors like me how we should do our jobs without really thinking for ourselves when Emma broke the silence in our living room.

“This is really interesting”, she said. “The way clicker training works may be by stimulating the amygdala of animals, so they feel instant joy before they consciously become aware that the trainer approves of what they just did.”

I knew a fair amount about clicker training; Emma has been using it on our canine family members and I have seen it work wonders with our adolescent female German Shepherd.

“Isn’t it just a conditioned response like Pavlov’s bell?” I asked as I looked up from my journal.

“Well, some people seem to think the actual sound of the clicker may be a more direct way to stimulate the amygdala than other sounds or words people use in training.”

My eyes moved from my wife’s face, framed by her beautiful long brown hair, to her eyeglasses reflecting the light from her computer screen, to the stack of books next to her. Suddenly my mind jolted at the title of the book on top. For a split second I thought it said:

How to Clicker Train Your Doc 

Emma was back to reading her webpage. The dogs snored peacefully. My mind was spinning.

Physicians are not quite subjected to clicker training, but we are certainly recipients of signals that are aimed at our preconscious minds, if not our amygdalas. All those people and institutions that try to influence physicians’ behavior are trying to get into our minds below the radar of our critical thinking, just like advertisers work on all of us. They use feel-good messages that try to do what clicker training does to our pets – create new behaviors we would otherwise not pick up on our own.

But doesn’t it go deeper than that for most doctors? It seems to me we often make ourselves do things that run counter to our nature. We do what others say we are good at, even when there’s no one around to cheer us on – even when doing it is to our own ultimate detriment. We end up using our burnout skills because we have created our own conditioned responses.

I opened my own laptop and started reading about clicker training and the amygdala. Wikipedia gave me the following quote:

“Clicker–trained animals become great problem–solvers, develop confidence, and perform their work enthusiastically.”

Just like doctors…


I just realized none of the posts show on an iPad or a computer, but they do show on an iPhone. WordPress is working on this. In the meantime, please visit my Substack.


Osler said “Listen to your patient, he is telling you the diagnosis”. Duvefelt says “Listen to your patient, he is telling you what kind of doctor he needs you to be”.


BOOKS BY HANS DUVEFELT, MD

CONDITIONS, Chapter 1: An Old, New Diagnosis

Top 25 Doctor Blogs Award

Doctor Blogs

Enter your email address to subscribe to this blog and receive notifications of new posts by email.

Mailbox

contact @ acountrydoctorwrites.com
Bookmark and Share
© A Country Doctor Writes, LLC 2008-2022 Unauthorized use and/or duplication of this material without express and written permission is strictly prohibited. Excerpts and links may be used, provided that full and clear credit is given.


